How Smaller Elderly Care Settings Improve Safety, Guidance, and Assistance
Business Name: BeeHive Homes of Granbury
Address: 1900 Acton Hwy, Granbury, TX 76049
Phone: (817) 221-8990
BeeHive Homes of Granbury
BeeHive Homes of Granbury assisted living facility is the perfect transition from an independent living facility or environment. Our elder care in Granbury, TX is designed to be smaller to create a more intimate atmosphere and to provide a family feel while our residents experience exceptional quality care. BeeHive Homes offers 24-hour caregiver support, private bedrooms and baths, medication monitoring, fantastic home-cooked dietitian-approved meals, housekeeping and laundry services. We also encourage participation in social activities, daily physical and mental exercise opportunities. We invite you to come and visit our assisted living home and feel what truly makes us the next best place to home.
1900 Acton Hwy, Granbury, TX 76049
Business Hours
Most families start exploring senior care after a scare: a fall in your home, a medication mix‑up, a wandering incident, or a progressive decline that suddenly becomes difficult to overlook. In those minutes, the world of assisted living and elderly care can feel like an alphabet soup of alternatives and sales language. Buried in the information is one factor that silently forms nearly everything about a resident's life: the size of the care setting.
Having worked with older adults in both large neighborhoods and small residential homes, I have seen the difference that scale makes. Larger is not automatically even worse, and smaller is not automatically much better. But when the top priority is safety, close guidance, and truly tailored support, thoughtfully run smaller settings have some structural benefits that are difficult to reproduce in a large structure with a hundred residents.
This does not imply everyone should rush towards the smallest home they can find. It implies households need to understand how size affects care, what trade‑offs are included, and how to inform a well run small environment from one that merely calls itself "cozy".
What "small" truly indicates in elderly care
People use the term "small" to explain whatever from a 20‑apartment assisted living wing to a four‑bed residential care home. To comprehend the effect on safety and supervision, it assists to draw some rough lines.
In lots of regions, senior care settings fall under 3 broad groups:
- Large communities: normally 60 to 200 citizens, frequently with numerous floors, dining spaces, and activity spaces.
- Mid sized centers: roughly 20 to 60 citizens, often a single building or wing, sometimes part of a bigger campus.
- Small residential settings: generally 3 to 16 homeowners, frequently licensed as adult household homes, board‑and‑care, residential care homes, or similar names depending upon the state or country.
The labels differ by jurisdiction, but the lived experience in a 10‑resident home is very various from that in a 120‑resident facility.
In a large assisted living community, the advantages normally center on facilities: restaurant‑style dining, regular activities, on‑site treatment, transport, and a sense of a "village" under one roof. The trade‑off is that personnel should cover a lot of ground. A caregiver might be accountable for 12 to 18 residents throughout a shift, sometimes more, typically scattered throughout a long corridor or several wings.
In a really small elderly care home, there might be 1 or 2 caretakers for 6 to 10 residents, all within view or just a brief corridor away. There is generally one cooking area, one main living location, and bedrooms nestled closely around them. What you quit in shiny amenities, you get in distance. That proximity is what translates into security and supervision.
Why physical scale shapes safety
When we talk about "security" in senior care, we are really discussing particular risks: falls, roaming and exit‑seeking, medication errors, choking and goal, delayed reaction in emergency situations, and undetected changes in health status. Size influences each of these, typically in subtle ways.
In a smaller setting, personnel can actually hear more. A chair scraping on tile, a closet door opening, a resident muttering in the corridor at 3 a.m. These small noises frequently precede an occurrence. In a large building with long hallways, heavy fire doors, and mechanical sound, those early cues are easy to miss.
One afternoon in a 9‑bed home, a caretaker I dealt with stopped briefly mid‑conversation and said, "That is not her typical cough." She strolled down the hall, checked on a resident, and found that she had begun aspirating on a sip of water. Quick intervention, urgent call to the doctor, health center visit, and the resident recuperated. Would that have been captured as quickly in a dining-room with 70 individuals talking over clattering meals? Potentially, but less likely.
Smaller environments also decrease the distance between risk and action. If a resident stands up unsteadily, a caregiver 3 steps away can offer an arm. In a big center, a resident may walk a surprising distance before anyone notices, specifically if staffing ratios are stretched at certain times of day.
None of this indicates large neighborhoods can not be safe. Many are, and they often have more electronic cameras, nurse coverage, and safety technology. However technology rarely makes up for the basic truth that in a smaller area, it is harder for an issue to stay concealed for long.
Staff presence and supervision
Supervision is not just about enjoying individuals; it is about knowing them all right to discover change. Smaller elderly care homes tend to create that familiarity by design.
In a 6 to 12 resident home, every caregiver normally understands:
- Each resident's common strolling speed and posture.
- How they like their coffee or tea.
- Which jokes land and which do not.
- What "typical" confusion appears like for that person and what feels off.
That accumulated understanding becomes an informal early‑warning system. A skilled caretaker in a small setting will often say things like, "She is quieter at breakfast today; something is developing" or "He generally sleeps after lunch, however he has actually been pacing for an hour." That type of pattern acknowledgment is much more difficult when a single person is handling 15 homeowners across 2 hallways.
Larger assisted living neighborhoods try to build guidance through systems: routine rounding, electronic care notes, occurrence reports, set up assessments. Those are necessary, but they can produce a rhythm where staff react to tasks rather than to people. In a small home, tasks are still there, however they are woven into common family life. Staff see residents from numerous angles in a single day: at the kitchen table, in the corridor, in the garden, throughout a television program. Supervision is developed into every interaction.
Families frequently see this distinction during respite care. A loved one may remain for 2 weeks in a 100‑resident community, then 2 weeks in an 8‑resident home. In the bigger neighborhood, the family might get a packet of notes, a care summary, and arranged updates. In the smaller home, they typically hear, "She has actually begun humming once again after lunch; she seems more relaxed" or "He is eating much better if we sit with him and serve smaller portions first." Both approaches have worth, however for vulnerable grownups with dementia, the granular observations often prevent larger problems.
Medication management and medical oversight
Medication mistakes are one of the most typical security threats in any senior care environment. Missing a dose of high blood pressure medicine might not cause an instant crisis. Doubling insulin or mismanaging blood thinners can.
In larger centers, medication management often depends on medication carts, set up "med passes," bar‑code scanning, and different medication service technicians. That structure can be very safe when staffing is stable and workflow is well organized. The danger begins busy shifts: a fire alarm, a fall, 3 residents asking for help at once, and a med tech fast moving through a long list.
In smaller settings, there is rarely a med cart rolling down halls. Medications are normally stored in a locked cabinet or room, and the very same caregivers who help with bathing and meals likewise manage routine meds, within their training and the policies of their region. The resident list is much shorter, the timing more flexible. Staff might give blood pressure tablets over breakfast, eye drops in the bathroom a couple of minutes later on, and prescription antibiotics throughout afternoon tea.

The safety benefit here comes from two elements. Initially, fewer locals mean fewer complex schedules to handle at once. Second, caretakers often see patterns quickly: "She is taking her tablets in the afternoon; we need to try considering that one squashed with applesauce" or "He looks off each time we increase that dosage." That feedback loop between observation and clinical adjustment tends to be tighter in a smaller environment, particularly when a nurse or physician is accessible and engaged with the home.
That said, tiny homes can fail if they do not have strong clinical oversight. Households need to ask how the home coordinates with physicians, who evaluates medications routinely, and how personnel are trained. A cottage without great systems can be more unsafe than a large community with robust medical protocols.
Fall risk and the design of everyday life
Falls hardly ever happen out of no place. They creep up through subtle shifts: a somewhat longer distance to the bathroom, a new thick carpet in the hallway, a chair placed a little too far from the table. In a large facility, upkeep and design decisions are produced dozens of individuals at the same time. That can work, however it inevitably means compromise.
In a small elderly care home, the physical environment is more like a basic home: less stairs, much shorter ranges, and normally one primary location where individuals collect. Personnel relocation through the same spaces continuously. If a rug starts to curl at the corner, someone typically journeys lightly or notices it within a day or two, not weeks later on throughout a main inspection.
The scale also permits practical customization. If a resident with Parkinson's freezes in narrow spaces, hallway furnishings can be reorganized rapidly. If someone with dementia puzzles the bathroom door, staff can include a colored indication or memory cue just for that person. These small environmental tweaks directly reduce fall threat and roaming without feeling institutional.
I keep in mind one resident, a former carpenter, who kept attempting to "fix" things in a big structure. In the smaller home he relocated to later, staff offered him a safe tool kit with blunt tools and small tasks: tightening up cabinet knobs, inspecting chair legs. His agitated walking became purposeful motion, and his fall events dropped over the next months. That sort of versatile response is a lot easier to attempt when you are handling a single living room, not a five‑floor complex.
Emotional security and the rhythm of the day
Physical safety is just half the story. Psychological security matters simply as much, especially for older adults dealing with memory loss, stress and anxiety, or depression.
Large communities generally work on schedules changed for operational efficiency. Breakfast from 7 to 9, activities at 10, lunch at 12, showers on appointed days, medication passes at set times. Lots of homeowners value the structure and variety, however certain people can feel swept along by a timetable that does not match their natural rhythm.
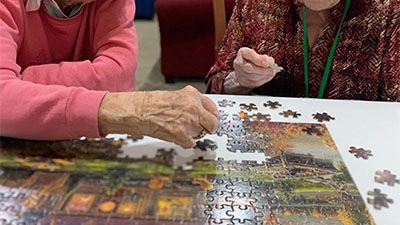
In a senior living small residential senior care home, the speed is more detailed to domestic life. If someone prefers coffee at 6 a.m. And breakfast at 9, it is easier to accommodate. If another resident sleeps badly and wants to sit quietly with a caregiver at 3 a.m. Enjoying old films, there is space for that without interrupting lots of others.
This flexibility has a direct impact on agitation, specifically in locals with dementia. When people are not constantly being rushed, lined up, or asked to adjust to group schedules, they tend to be calmer and less resistant. Less agitation ways fewer occurrences that intensify to physical restraint, sedating medications, or emergency situation transfers.
I have seen households surprised by how a parent's "behavior problems" soften in a small assisted living or board‑and‑care home. A woman who struck staff in a big memory care unit stopped doing so when she could eat in a small group at a home‑style table and invest afternoons folding towels in the kitchen area. The behavior had actually been an interaction of overwhelm, not an unchangeable personality trait.
The function of smaller settings in respite care
Respite care is typically the first real test of any elderly care arrangement. A brief stay provides everybody an opportunity to see how a setting manages unknown regimens, medical conditions, and emotional needs.
In a large assisted living or memory care neighborhood, respite stays can be extremely structured: official admission evaluations, printed care strategies, a set room for a limited time, often a minimum stay requirement. This works well for seniors who adjust quickly to new environments and take pleasure in activity calendars filled with options.
Smaller homes tend to integrate respite citizens straight into life. There may be a spare bed room that ends up being "Grandpa's space," with the same caregivers and routines as irreversible locals. On the very first day, personnel might take a seat with the family at the kitchen area table, review medications and choices, and see how the person moves, eats, and interacts.
For caregivers in the house who are currently stretched thin, sending a loved one to a small residential home for respite can feel closer to handing them to an extended household. That sense of connection impacts how willingly older adults accept the break. A guy who declined respite in a large structure with hectic passages sometimes consents to "remain for a couple of days in that house with the garden and friendly pet."
Respite is likewise where supervision quality ends up being visible rapidly. Households returning after a week can pick up on information: Is the laundry done and identified effectively? Does their loved one keep in mind staff names and feel at ease? Does the staff recount particular occasions and choices, or just describe generic "She did great"?
Family participation and transparency
One of the quiet strengths of smaller elderly care homes is the transparency that includes minimal space. Families see more of what happens, good and bad.
When you stroll into a big senior care center, you typically go through a lobby, maybe a receptionist, then down corridors to a resident's room. You see a piece of life: a few staff, some residents in typical areas, decor, published menus and calendars. Much occurs behind doors and on other floors.
In a smaller home, you frequently step straight into the primary living location. The kitchen area smells are right there. You can hear how personnel speak to citizens, notice whether call lights are going unanswered, and see who is really on shift. If something feels off, it is tough for the environment to hide it.
This visibility can reinforce collaboration. Families are more likely to have informal chats with caregivers, share observations, and change care together. That continuous conversation normally catches issues early: skin changes, mood shifts, household dynamics, monetary questions. It also builds trust, which is crucial when tough choices emerge about hospitalizations, hospice, or transitions.
Trade offs and limitations of smaller settings
Small does not imply perfect. Every design of senior care has trade‑offs, and it is important to look at them honestly.
One obstacle is staffing depth. A big assisted living community with 80 homeowners might have a nurse on site every day, plus several caregivers, med techs, and backup staff. If somebody contacts ill, there is generally a pool to draw from. In a 6‑resident home, losing even one caregiver to disease can strain the group if there is not a solid backup plan.
Another problem is access to on‑site services. Larger structures may offer on‑site physical therapy, going to professionals, pharmacy delivery several times a day, and transportation vans. A small residential care home may rely more on outdoors service providers can be found in or households organizing appointments. For extremely medically complicated citizens, that additional coordination can be a burden.
Social range is also different. Some outgoing elders prosper in a big community with dozens of possible good friends and several activities every day. They take pleasure in the sensation of "going out" to concerts, lectures, and workout classes without leaving the building. In a small home, the social circle is intimate. For some, that feels like household. For others, it can feel limiting.
Regulation and oversight can differ also. In numerous regions, small centers are certified under various classifications with different inspection frequencies. Some are outstanding and firmly run; others cut corners. Families can not assume that "home‑like" instantly indicates "high quality."
The key is to match the setting to the individual's needs and personality, and after that evaluate the real operation of the home, not simply its size.
A quick contrast: where small settings often excel
Used thoroughly, a concise comparison can clarify where small elderly care homes tend to have an edge. For lots of locals with safety and guidance needs, smaller environments usually offer:
- Shorter action times when someone needs help or an alarm sounds.
- Closer observation and earlier detection of changes in health or behavior.
- More versatile daily regimens that decrease agitation and resistance.
- Stronger staff‑resident relationships, leading to customized support.
- Easier family interaction and higher openness day to day.
These are propensities, not guarantees. Some large communities work hard to match and even surpass these qualities. Still, the structural advantages of proximity and familiarity are hard to ignore.
How to examine a small elderly care home
For households thinking about a transfer to a smaller setting, the secret is not only "Is it small?" but "Is it well run, safe, and lined up with our needs?" It assists to ground the search in a brief mental checklist during visits.
Here is one simple method to focus your attention while touring or arranging respite care:
- Watch how staff talk to residents: tone, perseverance, eye contact, and whether they use names.
- Notice smells and sounds: strong odors, continuous alarms, or raised voices can indicate problems.
- Ask particular questions about staffing ratios on nights and weekends, not simply weekdays.
- Look for detailed understanding: can staff explain each resident's choices and health issues?
- Clarify how emergencies, hospital transfers, and interaction with households are handled.
You are not just purchasing a room; you are signing up with a small community. The quality of that ecosystem will shape your loved one's safety and sense of home more than any brochure.
Where smaller settings fit in the larger senior care landscape
Elderly care is hardly ever a straight line. Numerous older adults move between levels and types of care over time: independent living, assisted living, memory care, health center stays, knowledgeable nursing, and hospice. Small residential homes and intimate assisted living settings fill a crucial specific niche in that landscape.
For those who are too frail or cognitively impaired to live alone, but who do not require the intensity of a nursing home, a small setting can supply the best level of structure and guidance without compromising self-respect and uniqueness. For family caretakers nearing burnout, a brief respite in a small home can avoid crisis and extend the possibility of continued care at home.
The trend in lots of areas has actually been a progressive shift toward these "home within a home" designs. Some big schools now design their memory care or high‑acuity assisted living as clusters of small households under one bigger umbrella. Each household might host 10 to 14 citizens, with its own cooking area and care group. That hybrid approach attempts to mix the intimacy of small homes with the resources of a big organization.
At its best, elderly care is not about structures at all. It is about relationships, regimens, and actions to vulnerability. Smaller settings, when thoughtfully staffed and well controlled, often make those human elements much easier to deliver. They develop environments where staff can genuinely understand citizens, where families can stay carefully involved, and where safety is the result of constant, peaceful listening rather than periodic crisis response.
For households standing at the crossroads of senior care decisions, taking note of size is not a small information. It is a practical method to anticipate how well a setting will protect your loved one from preventable damage, how closely they will be supervised, and how personally they will be supported in the daily organization of living the later chapters of their life.

BeeHive Homes of Granbury provides assisted living care
BeeHive Homes of Granbury provides memory care services
BeeHive Homes of Granbury provides respite care services
BeeHive Homes of Granbury supports assistance with bathing and grooming
BeeHive Homes of Granbury offers private bedrooms with private bathrooms
BeeHive Homes of Granbury provides medication monitoring and documentation
BeeHive Homes of Granbury serves dietitian-approved meals
BeeHive Homes of Granbury provides housekeeping services
BeeHive Homes of Granbury provides laundry services
BeeHive Homes of Granbury offers community dining and social engagement activities
BeeHive Homes of Granbury features life enrichment activities
BeeHive Homes of Granbury supports personal care assistance during meals and daily routines
BeeHive Homes of Granbury promotes frequent physical and mental exercise opportunities
BeeHive Homes of Granbury provides a home-like residential environment
BeeHive Homes of Granbury creates customized care plans as residents’ needs change
BeeHive Homes of Granbury assesses individual resident care needs
BeeHive Homes of Granbury accepts private pay and long-term care insurance
BeeHive Homes of Granbury assists qualified veterans with Aid and Attendance benefits
BeeHive Homes of Granbury encourages meaningful resident-to-staff relationships
BeeHive Homes of Granbury delivers compassionate, attentive senior care focused on dignity and comfort
BeeHive Homes of Granbury has a phone number of (817) 221-8990
BeeHive Homes of Granbury has an address of 1900 Acton Hwy, Granbury, TX 76049
BeeHive Homes of Granbury has a website https://beehivehomes.com/locations/granbury/
BeeHive Homes of Granbury has Google Maps listing https://maps.app.goo.gl/xVVgS7RdaV57HSLu9
BeeHive Homes of Granbury has Facebook page https://www.facebook.com/BeeHiveHomesGranbury
BeeHive Homes of Granbury has an YouTube page https://www.youtube.com/@WelcomeHomeBeeHiveHomes
BeeHive Homes of Granbury won Top Assisted Living Homes 2025
BeeHive Homes of Granbury earned Best Customer Service Award 2024
BeeHive Homes of Granbury placed 1st for Senior Living Communities 2025
People Also Ask about BeeHive Homes of Granbury
What is BeeHive Homes of Granbury Living monthly room rate?
The rate depends on the level of care that is needed. We do an initial evaluation for each potential resident to determine the level of care needed. The monthly rate is based on this evaluation. There are no hidden costs or fees
Can residents stay in BeeHive Homes until the end of their life?
Usually yes. There are exceptions, such as when there are safety issues with the resident, or they need 24 hour skilled nursing services
Do we have a nurse on staff?
No, but each BeeHive Home has a consulting Nurse available 24 – 7. if nursing services are needed, a doctor can order home health to come into the home
What are BeeHive Homes’ visiting hours?
Visiting hours are adjusted to accommodate the families and the resident’s needs… just not too early or too late
Do we have couple’s rooms available?
Yes, each home has rooms designed to accommodate couples. Please ask about the availability of these rooms
Where is BeeHive Homes of Granbury located?
BeeHive Homes of Granbury is conveniently located at 1900 Acton Hwy, Granbury, TX 76049. You can easily find directions on Google Maps or call at (817) 221-8990 Monday through Sunday 9:00am to 5:00pm
How can I contact BeeHive Homes of Granbury?
You can contact BeeHive Homes of Granbury by phone at: (817) 221-8990, visit their website at https://beehivehomes.com/locations/granbury/, or connect on social media via Facebook or YouTube
You might take a short drive to the Granbury Opera House. The Granbury Opera House hosts performances and classic productions that can be enjoyed by residents in assisted living or memory care during senior care and respite care outings.